Lateral Extra-Articular Tenodesis (LET) in ACL Reconstruction — Reading
Lateral Extra-Articular Tenodesis (LET) is an adjunct procedure performed alongside ACL reconstruction to improve rotational control of the knee and reduce the risk of graft re-injury.
Mr Sam Nahas, consultant knee surgeon at Circle Reading Hospital, offers LET as part of selected primary and revision ACL reconstructions, particularly in patients with high-demand, pivoting sports or significant rotational instability.
At a glance
- Who it is for
- Added to some ACL reconstructions: revision surgery, marked rotational instability, pivoting sports, generally loose ligaments, or young athletes at risk of re-injury.
- Anaesthetic
- Usually general anaesthetic.
- Walking
- Most walk the same day; weight bearing immediately or within days.
- Back to desk work
- 2 weeks.
- Sport
- Jogging at around 4 months; return to sport typically at 9–12 months.
- Patient rating
- 5.0 out of 5 from 31 verified patient reviews on Doctify.
- Waiting time
- New patients are usually seen within a week.
- Cost
- Self-pay consultation £400, with a fixed price for surgery quoted after your consultation. Insured patients need a GP referral.
Understanding LET
During ACL reconstruction, the main ligament inside the knee is replaced to restore anterior stability. In some knees, particularly after major injuries or re-rupture, there is also excessive outward (rotational) movement.
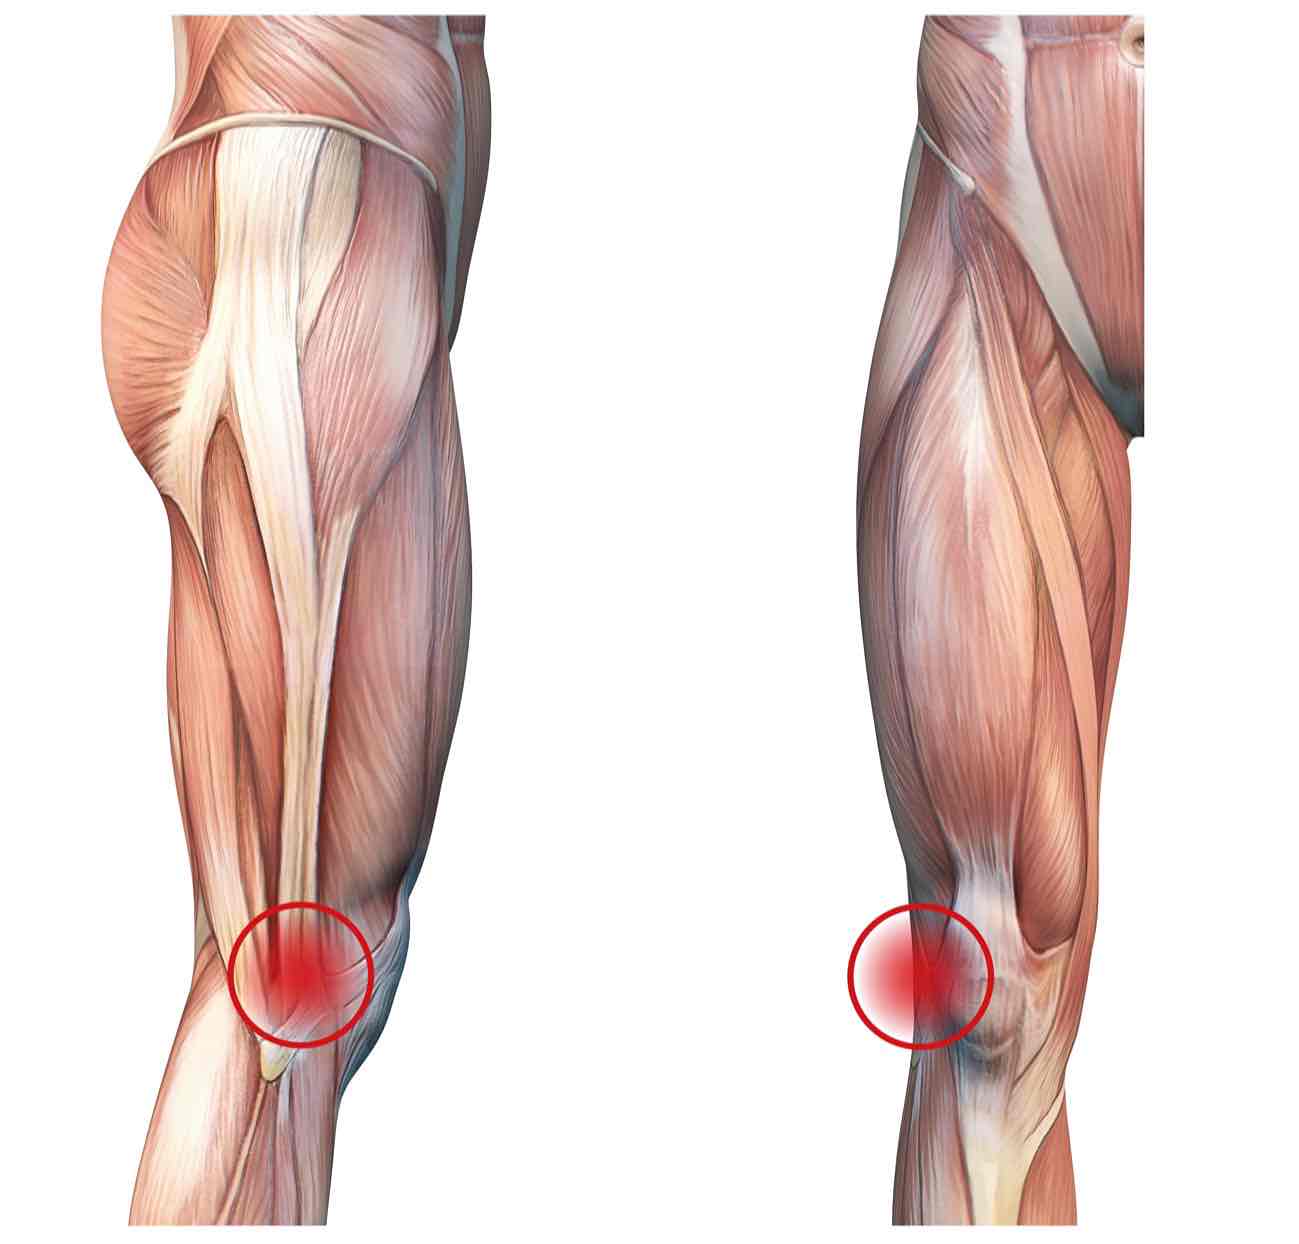
LET involves reinforcing the outer (lateral) side of the knee using a strip of tissue from the iliotibial band. This additional stabilisation helps control rotational movement, protecting the new ACL graft and enhancing knee stability.
Who benefits from LET
Mr Nahas may recommend a lateral extra-articular tenodesis in the following scenarios:
Revision ACL reconstruction (repeat ACL surgery)
Marked rotational instability on examination (pivot shift)
High-demand pivoting or cutting sports (football, rugby, netball, skiing)
Generalised ligamentous laxity
Young, active athletes at risk of reinjury
LET is performed through an additional incision on the outside of the knee and although it will slow down the initial rehabilitation, it does not significantly alter overall recovery time.
How LET is performed
A thin strip of the iliotibial band (ITB) is detached near the knee and passed under a nearby ligament to reinforce the outside of the knee. This limits excessive rotation while allowing normal knee motion.
The technique is usually combined with ACL reconstruction during the same operation.
The procedure is usually performed under general anaesthetic at Circle Reading Hospital, with most patients walking the same day.
Evidence supporting LET
Recent randomised controlled trials and registry data have shown that adding LET to ACL reconstruction can significantly reduce the risk of graft rupture and re-injury, particularly in high-risk patients.
STABILITY-1 (Getgood et al., American Journal of Sports Medicine, 2020)—the largest randomized study of its kind—showed that adding a lateral extra-articular tenodesis (LET) to anterior cruciate ligament reconstruction (ACLR) reduced the 2-year "clinical failure" (persistent rotatory laxity or graft rupture) by a relative risk of 38%. It also reduces graft ruptures by ~67%. Subsequent systematic reviews corroborate that LET, in appropriately selected high-demand patients, lowers re-injury and residual pivot-shift.
Recovery and rehabilitation
Rehabilitation after ACL reconstruction with LET follows the same general timeline as standard ACL surgery:
Weight bearing
Immediately or within days
Return to office work
2 weeks
Jogging
Around 4 months
Return to sport
Typically 9–12 months
Each patient follows a recovery pathway designed for safe healing and return to full activity. The recovery pathway is tailored to each individual's lifestyle and sporting goals. Recovery is criteria-based and not actually based on a fixed time. What this means is you are not allowed to progress to the next phase of rehabilitation if your knee or muscles are not ready. Each patient's timeline will differ depending on progress, and results are not guaranteed as per this timeline. These are approximate estimates.
Risks and complications
As with any operation, there are risks. Because LET is done at the same time as ACL reconstruction, the risks of both apply. Most patients have no serious problems, but it is important to know about them.
Infection of the wound or the knee joint
Blood clots in the leg (DVT) or lungs (pulmonary embolism)
Bleeding or bruising, including a collection of blood (haematoma) under the outer scar
Numbness around the scars
Risks from the anaesthetic
Pain or irritation on the outer side of the thigh or knee, sometimes from the fixation
Stiffness of the knee
The risks of ACL reconstruction, including the new graft tearing again
Mr Nahas will go through the risks that apply to you at your consultation.
Expertise in modern ACL techniques
Mr Nahas performs ACL reconstruction with LET for selected cases where enhanced rotational stability is needed, some examples of which include: revision, in specific anatomical circumstances and elite-sport knees.
His practice is guided by cutting-edge research, including the SNNAP and STABILITY trials.
Self-pay and appointments
Self-pay consultations are available for within a week access for assessment, and MRI, with short wait times for surgery.
Where surgery is performed
All procedures are undertaken at Circle Reading Hospital, serving patients across Berkshire, Wokingham, Henley, Oxford, and surrounding areas.